
Anal Cytology
Anal cytology, also known as an anal Pap test, detects early cellular changes that could one day develop into anal cancer.
According to the American Cancer Society, anal cancer is still relatively rare compared to colon or rectal cancer. But cases have been steadily increasing, especially among people living with HIV and others with weakened immune systems.1
What Is Anal Cytology?
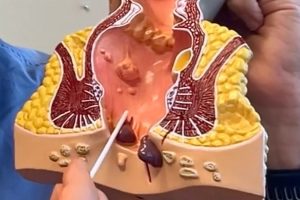
Anal cytology works much like a cervical Pap smear. A small, moistened swab is inserted a few centimeters into the anus to collect cells from the lining of the anal canal – it takes a minute or two during a routine visit and requires no anesthesia. Those cells are then sent to a lab, where they’re examined under a microscope to look for abnormalities.
The anal canal is lined with cells that can become infected with the human papillomavirus (HPV), the same virus responsible for most cervical cancers. Detecting abnormal cells early through cytology means precancerous or cancerous changes can be addressed before they progress.
The procedure is quick and only mildly uncomfortable for most people, and you don’t need sedation or downtime afterward.
 What Does It Check For?
Anal cytology looks for abnormal or precancerous cells in the anal canal. These cellular changes are usually caused by HPV, a common sexually transmitted infection that nearly all adults will contract at some point in their lives.
In most people, the immune system clears HPV naturally.2 But in others, especially those with compromised immunity, the infection can linger and lead to anal intraepithelial neoplasia (AIN), a precancerous condition. Left untreated, AIN can progress into anal cancer over time.
When a cytology result is “positive” or “abnormal,” it means the lab found cells that don’t look normal, and that doesn’t automatically mean cancer. But it does mean follow-up testing is needed.
Who Should Get an Anal Cytology Test?
Anal Pap testing isn’t recommended for everyone. It’s primarily used to screen people who have a higher risk of anal cancer. The International Anal Neoplasia Society (IANS) 2024 consensus guidelines recommends testing for the following:3
- Men who have sex with men (MSM) and transgender women living with HIV: start screening at age 35.
- All other people living with HIV and MSM/transgender women without HIV: start at age 45.
- Solid-organ transplant recipients: start 10 years after transplant.
- History of vulvar precancer/cancer: start within 1 year of diagnosis.
- Over age 45 with one of the following (using shared decision-making): prior cervical/vaginal HSIL (high-grade squamous intraepithelial lesions) or cancer, persistent cervical HPV-16 for over one year, perianal warts, or certain autoimmune conditions.
Anal cancer is more common in older adults, with most diagnoses occurring after age 50, but screening can start between ages 25 and 45, depending on individual risk factors. Intervals after the initial testing will be discussed with your provider and based on your unique circumstances.
What Happens If the Test Is Positive?
A positive or abnormal anal cytology result means your provider will want to take a closer look at the tissue. Depending on the specific result (for example, ASC-US/LSIL/HSIL) and any hrHPV result, we may:
- Repeat cytology/high-risk HPV at a defined interval
- Perform high-resolution anoscopy (HRA) to examine areas more closely and/or perform a biopsy
- Treat biopsy-proven HSIL (high-grade squamous intraepithelial lesions, e.g., precancerous cells)
An important study called the ANCHOR trial showed that treating HSIL in people living with HIV reduced the risk of anal cancer by more than half, which is why we now emphasize finding and managing HSIL.4
If biopsy results show cancer, your healthcare team will order imaging tests, such as CT, PET-CT, or MRI, to learn more about size, location, and whether it has spread.
Risk Factors and Prevention
Multiple determinants influence the risk of developing anal cancer, yet more than 93% of anal cancer cases are caused by HPV, making it the most significant risk factor.5
Additional factors include:
- HIV infection: Due to the advent and success of HIV medications, treatment has transformed HIV into a manageable condition, yet the virus and associated medications weaken the immune system. Immunosuppression makes it harder for the body to clear HPV infections, allowing the virus to persist and cause more significant cellular damage.
- Other HPV-related cancers: HPV spreads easily, between sexual partners as well as within the host body. Because of the proximity of the anus to the vulva, those who’ve had cervical, vaginal, or vulvar cancer are more likely to develop anal cancer.
- Age and gender: Most cases occur in people over 50, and incidence is higher in white women and black men; in general, there is a slightly higher incidence in women, with new cases in 2024 more than doubling that of men.6
- Smoking: The carcinogenic elements of cigarette smoke are not confined to the mouth, throat, and lungs; the entire body is susceptible. Smoking weakens immune function and increases the chances of having HPV-related cancers.
- Weakened immune system: Whether due to HIV, organ transplantation, or autoimmune disease, reduced immunity allows HPV to persist longer in the body. As the virus lingers, it interferes with the normal life cycle of cells, causing genetic changes that prevent damaged cells from dying when they should. Over many years, this buildup of abnormal cell growth can develop into precancerous changes and, if left untreated, may progress to cancer.
- Multiple sexual partners: Having multiple sexual partners increases exposure to different strains of HPV, which raises the likelihood of infection and reinfection. Each new exposure gives the virus another opportunity to take hold, especially if the immune system is compromised or unable to fully clear previous infections.
Being honest about your sexual activity and lifestyle habits (e.g., diet, exercise, smoking) is an integral part of protecting your health. Your healthcare provider’s purpose isn’t to judge your choices or preferences – we’re here to help you stay healthy and informed. Open conversations about your sexual history, partners, and practices give your provider the information necessary for recommending the right tests and prevention strategies, such as:
- HPV vaccination
- Safe sex education
- Regular screening
- HIV management
- Smoking cessation
No matter your lifestyle or proclivities, you deserve care that’s confidential, respectful, and focused on your well-being.
If you notice symptoms like anal bleeding, discharge, itching, pain, pressure, constipation, or a lump near your anus, don’t wait – see your doctor for evaluation right away. Since there are no universal screening guidelines, talking with your colorectal healthcare provider about your individual risk can help determine whether anal cytology makes sense for you.
Note: Condom use is always recommended to reduce the risk of sexually transmitted infections. However, condoms aren’t 100% effective at preventing HPV transmission because the virus can spread through skin-to-skin contact in areas not covered by a condom. Get tested for STIs on a regular basis if you’re at risk, and have the conversation with your partner(s) about being tested.
Common Questions
What does anal cytology involve?
Expect for the test to take place during a routine office visit, and that it will only take a couple minutes. No prep is needed, you will not be sedated, and mild pressure or brief discomfort is common; most people resume normal activities immediately.
Is anal cytology for everyone?
No. It’s aimed at higher-risk groups (see “Who should be screened?”). Talk with us about your individual risk and local access to high-resolution anoscopy (HRA) before starting.
How often is screening done?
Intervals depend on your risk category and results (for example, annual vs. longer if repeatedly normal). We tailor this to you and to the tests available (cytology, hrHPV, co-testing) in our clinic.
If my result is abnormal, do I have cancer?
Usually not. It means we’ll do closer follow-up, often with high-resolution anoscopy (HRA), and only treat if biopsy shows HSIL (precancer) or cancer. Treating HSIL lowers cancer risk.
What is high-resolution anoscopy (HRA)?
High-resolution anoscopy (HRA) is the most accurate test for detecting anal precancer. Precancerous changes are called anal intraepithelial neoplasia (AIN). AIN is categorized as low-grade (AIN 1) or high-grade, also called high-grade squamous intraepithelial lesions (HSIL). HSIL is the type of abnormality that can progress to anal cancer if left untreated.
HRA is considered the gold standard for identifying AIN/HSIL and early anal cancer. It uses a small anoscope and high magnification to visualize subtle abnormal areas that cannot be seen with routine exams. HRA is performed in the office and typically takes 10–20 minutes.
What can you expect with ongoing surveillance?
If HRA and biopsy confirm HSIL, treatment is typically recommended. Because HPV can persist for years or recur and HSIL can recur even after treatment, ongoing surveillance is essential to detect changes before they become cancer. Possible scenarios include:
- After HSIL treatment:
- First surveillance at six months after treatment
- Ongoing surveillance every 6 to 12 months
- Cytology and/or hrHPV testing may supplement surveillance depending on risk
- If HSIL is present but not treated (rare situations):
- HRA is performed every six months to monitor for progression
- Treatment is recommended if lesions grow, become symptomatic, or show worrisome features
- After several normal HRAs:
- Surveillance may be extended to every two to three years, depending on immune status, HPV persistence, and provider judgement
- If cytology and hrHPV remain consistently negative:
- Some high-risk patients may transition to screening every 12 to 24 months, and with HRA only if a future test becomes abnormal
- American Cancer Society. (2024, January 17). Key Statistics for Anal Cancer. Www.cancer.org. https://www.cancer.org/cancer/types/anal-cancer/about/what-is-key-statistics.html.
- Anal Cancer Foundation. (2025b). Anal Cancer: Signs, Symptoms, Causes & Treatment. The Anal Cancer Foundation. https://www.analcancerfoundation.org/what-is-anal-cancer/.
- Stier, E. A., Clarke, M. A., Deshmukh, A. A., Wentzensen, N., Liu, Y., Poynten, I. M., Cavallari, E. N., Fink, V., Barroso, L. F., Clifford, G. M., Cuming, T., Goldstone, S. E., Hillman, R. J., Rosa‐Cunha, I., La Rosa, L., Palefsky, J. M., Plotzker, R., Roberts, J. M., & Jay, N. (2024). International Anal Neoplasia Society’s consensus guidelines for anal cancer screening. International Journal of Cancer, 154(10). https://doi.org/10.1002/ijc.34850.
- The Anchor Study. (2024). Homepage | The Anchor Study. Anchorstudy.org. https://anchorstudy.org/. “This study is funded by a grant from the National Cancer Institute of the National Institutes of Health under an award to the AIDS Malignancy Consortium.”
- Anal Cancer Foundation. (2025). Anal Cancer Risk Factors & Prevention. The Anal Cancer Foundation. https://www.analcancerfoundation.org/what-is-anal-cancer/prevention/.
- American Cancer Society. (2024, January 17). Key Statistics for Anal Cancer. Www.cancer.org. https://www.cancer.org/cancer/types/anal-cancer/about/what-is-key-statistics.html.